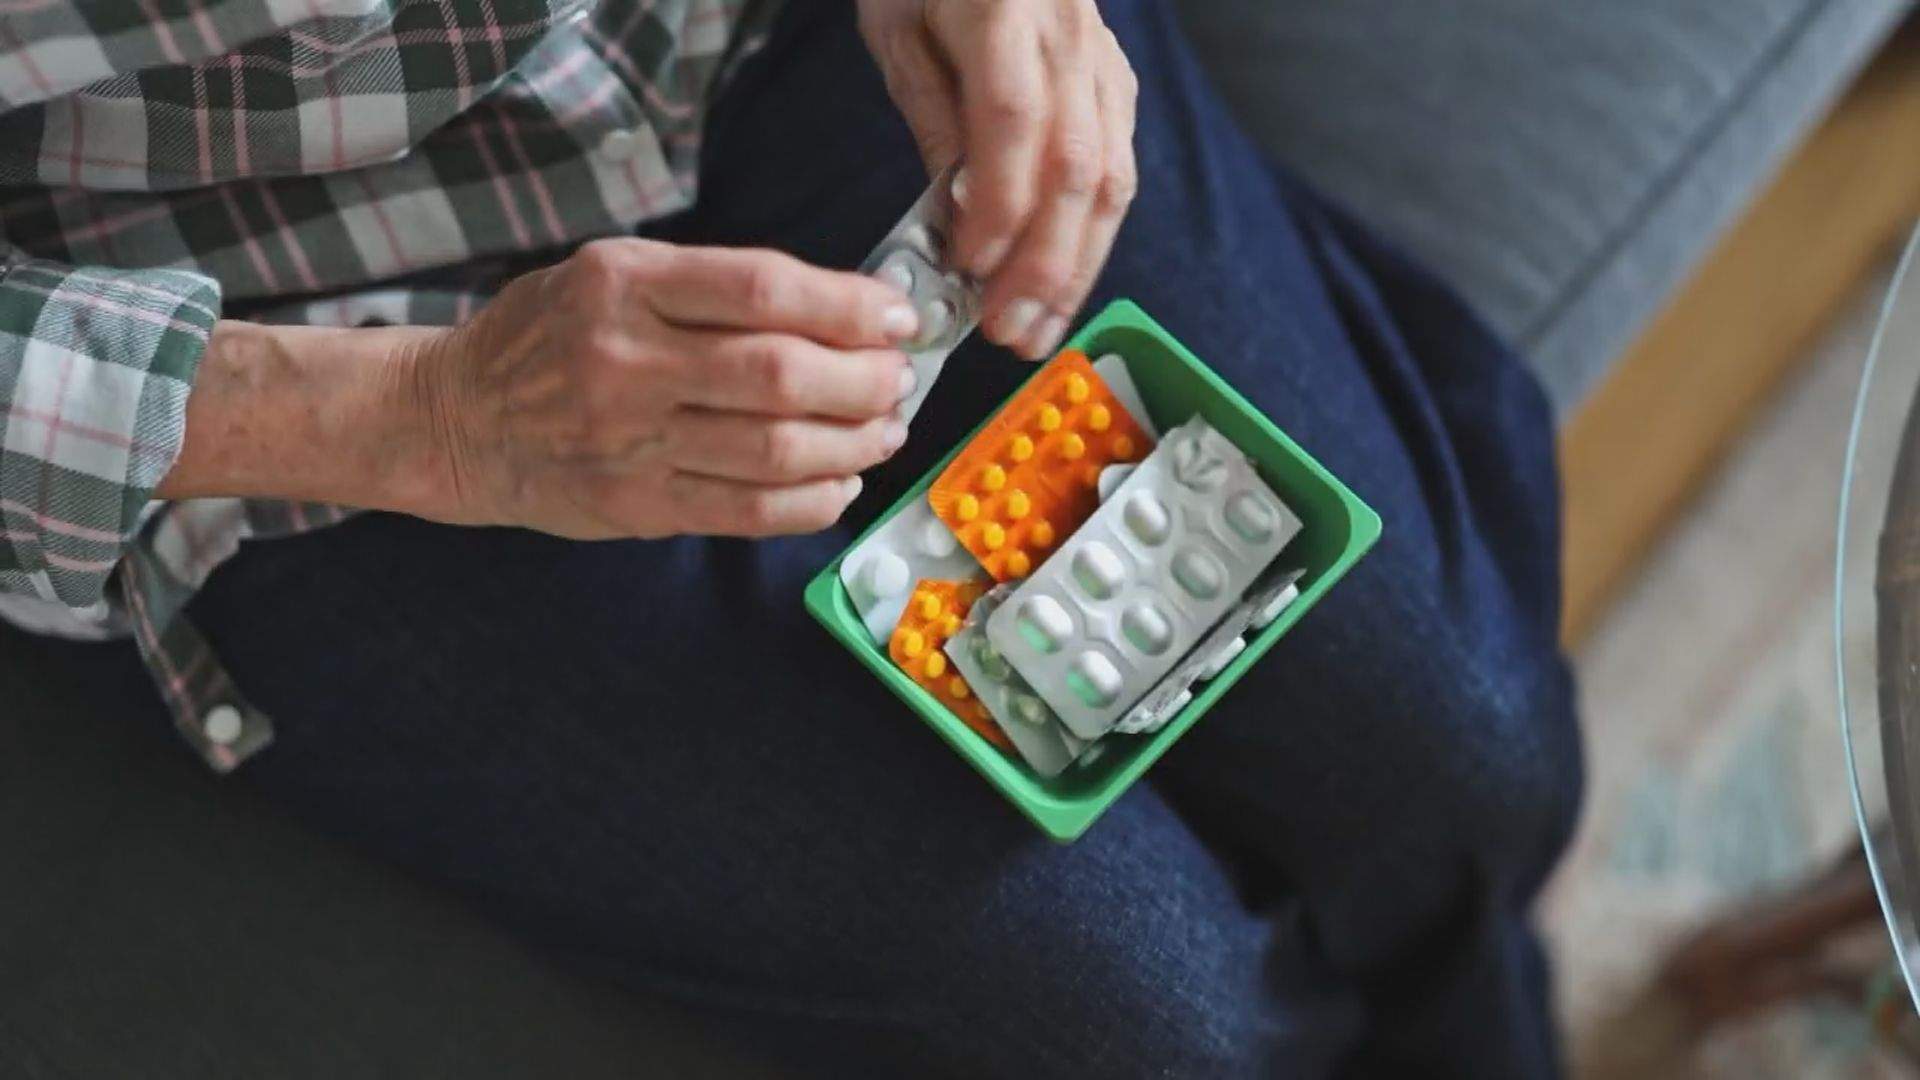
When people picture the opioid crisis, they picture teenagers or young adults in urban alleys. That mental image is completely outdated. Right now, a quiet medical emergency is playing out across living rooms and retirement communities throughout the province. Older adults are struggling with substance use at an unprecedented rate, and the healthcare system isn't ready for it.
Data released by the Ontario Drug Policy Research Network (ODPRN) at St. Michael's Hospital reveals a staggering reality. Healthcare interactions related to opioid use disorder among adults aged 55 and older more than doubled over an eight-year stretch, rising from 7,116 individuals in 2017 to 15,231 people. This isn't just a minor statistical blip. It is a fundamental shift in who is vulnerable to addiction, exposing major blind spots in how medical professionals treat aging populations.
How the Crisis Reached Living Rooms
Most seniors didn't wake up one day and decide to seek out street drugs. Decades ago, chronic pain management looked entirely different. During the heavy prescription eras of the 1990s and 2000s, doctors handed out powerful painkillers for routine joint pain, arthritis, and back injuries without fully understanding long-term dependency risks.
As prescribing guidelines tightened up in the 2010s, many patients found their legal prescriptions abruptly cut off or reduced. Left managing severe, unyielding chronic pain, a subset of these aging individuals transitioned toward the unregulated drug market.
Researchers point out that this is an aging-in-place crisis. Roughly 80 percent of fatal opioid toxicities among older adults happen inside private residences. Even more alarming? Only about one in five of those deaths occur with another person present who could step in with naloxone or call for help. People are suffering—and dying—entirely alone behind closed doors.
The Fentanyl Shift and the Danger of Isolation
The street supply has changed drastically. Fentanyl's involvement in opioid-related deaths among older adults doubled from 31 percent in 2017 to 62 percent. When a toxic, unpredictable supply meets an aging body that metabolizes drugs much slower than it used to, the margin for error shrinks to zero.
Age-related biological changes mean that standard doses hit older organs much harder. Kidneys and livers process substances with less efficiency. A dose that a younger person might survive can easily prove fatal for someone in their sixties or seventies.
Compounding this physical vulnerability is profound social isolation. Widowed seniors living alone often lack a daily support network. If they make a mistake with medication or experiment with an outside supply to manage sleepless nights or severe arthritis, nobody is there to notice the warning signs.
Why Long-Term Care Tells a Different Story
You might assume that nursing homes and long-term care facilities are epicenters for this crisis. The data says otherwise.
Throughout the study period, the number of older adults with opioid use disorder living in long-term care remained remarkably low, hovering under 130 individuals total. That stark contrast exposes a demographic divide. The crisis is heavily concentrated among independent seniors aging in private homes.
Institutional settings have strict medication distribution oversight. Independent living offers freedom, but it also strips away daily medical supervision. When an older adult living alone struggles with cognitive decline or unmanaged pain, they slip straight through the cracks of the medical establishment.
Fixing a Blind Spot in Healthcare
The medical community treats addiction as a young person's issue. Clinics, outreach programs, and harm reduction initiatives are rarely designed with a 70-year-old in mind.
Opioid agonist treatment utilization has climbed significantly, with recipients aged 55 and older rising from 2,661 to 13,370. Yet, general healthcare infrastructure still lacks age-sensitive addiction care. Providers need to screen older patients for substance risks during routine checkups, keeping in mind that pain management and dependency often hide behind polite smiles and closed doors.
Ignoring this demographic reality will only lead to more preventable deaths. It is time to look past old stereotypes and start treating the actual population that is hurting.



